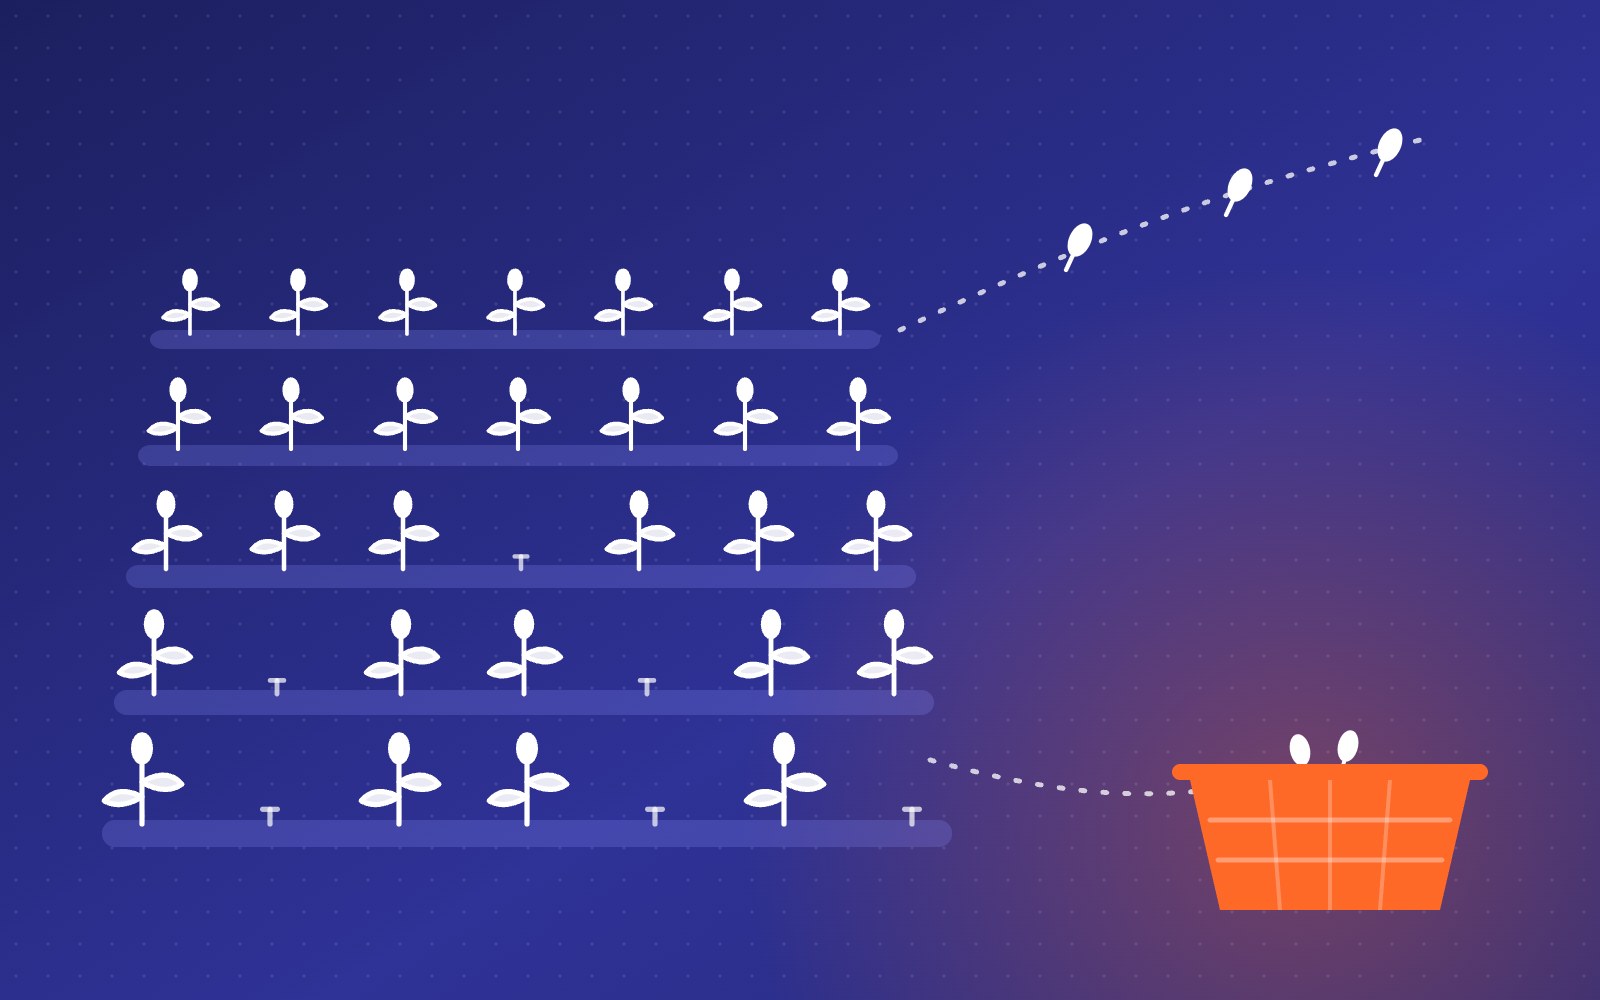
Picture a farmer who ploughs, plants, weeds and waters for three years. The crop comes up strong. Then, at harvest, he leaves a third of it standing in the field, complains that the neighbours are picking his maize, and tells everyone the family is going hungry because the land is poor.
Nobody would call that a shortage of food. We would call it a failure to harvest.
That, I am sorry to say, is a fair picture of Africa’s health workforce today.
The story we usually tell
The conventional story is familiar, and I have told parts of it myself. Africa does not have enough doctors, nurses and midwives. Rich countries recruit the ones we have. The brain drain empties our wards. Therefore we must slow the drain.
There is truth in it. The World Health Organization’s 2023 health workforce support and safeguards list named 55 countries whose density of doctors, nurses and midwives falls below the global median, and 37 of them are in Africa. Nigeria and Ghana are both on it.
The migration is real too. In the year to 31 March 2026, Nigeria and Ghana were the second and third largest sources of internationally educated nurses and midwives joining the UK register, with 1,614 and 1,391 new joiners respectively, according to the Nursing and Midwifery Council’s 2026 data report. Nigeria Health Watch reports that the country reportedly lost 75,000 nurses between 2020 and 2025.
So far, so familiar. Now look at the number that does not fit the story.
The number that changes the diagnosis
In May 2026, the WHO Regional Office for Africa published State of the Health Workforce in Africa 2026: Plan. Train. Retain. It found that the region’s health workforce grew from 4.3 million in 2018 to 5.72 million in 2024, and that the region still has only about 46% of the health workers it needs.
And then this: an estimated 943,000 trained health workers in the region were unemployed in 2024.
Read that again. Almost a million people whom our countries paid to train, in nursing schools, medical schools and midwifery colleges, were not working in health. To put that in perspective, it is more than 80 times the 10,961 internationally educated professionals who joined the UK register in the year to March 2026.
The detail is worse. Reporting on the region’s new workforce agenda, Down To Earth notes that average health worker unemployment is about 27%, and that unemployment among new graduates ranges from 46% to 69%. Graduates who cannot find a post in their own country are not being stolen. They are being left in the field.
WHO’s Regional Director for Africa, Dr Mohamed Yakub Janabi, put it plainly at the launch: “Africa’s health workforce crisis is no longer defined by scarcity alone, but by systemic failure.” Ghana’s Minister of Health, Kwabena Mintah Akandoh, said it more briefly still: “training alone is not enough.”
The strongest objection
The fairest objection is that unemployment and migration are the same problem, seen from two sides. If there are no funded posts at home, of course people leave. Blaming governments for not hiring, the argument goes, ignores the fact that they cannot afford to.
I accept the first half. The same WHO report found that nearly 46% of health workers say they intend to migrate. A nurse who waits two years for a posting, or who works unpaid as a volunteer in the hope of one day being absorbed, is making a rational choice when she buys a plane ticket. Nobody should be fenced in. As the Nursing and Midwifery Council itself says, nurses and midwives remain free to choose where they practise.
But the affordability argument deserves more scrutiny than it usually gets. WHO estimates that closing the gap would require about US$4 more per person per year, and that every dollar invested can return up to ten times in financial terms. That is not a small sum for a strained budget. It is a very small sum compared with the cost of training a nurse and then leaving her idle.
Training without hiring is the most expensive option of all. We pay for the seed, the water and the labour, and then we let the crop rot.
What the destination countries owe
None of this lets the wealthy countries off the hook. The WHO’s State of the World’s Nursing 2025 found that one in seven nurses worldwide is foreign-born, rising to 23% in high-income countries, against 3% in low-income ones. WHO called on high-income countries to review their reliance on foreign-trained nurses and to strengthen bilateral agreements with source countries.
That is the right ask. If you harvest from your neighbour’s field, you should help pay for the seed. Agreements that fund training places, share costs or support return should be the norm, not the exception.
But I will not build an argument for Africa’s health systems that depends on London or Washington changing its mind. We have seen how quickly that kind of support can disappear.
A policy is not a payroll
Some governments are moving. In August 2024, Nigeria approved a National Policy on Health Workforce Migration, designed to improve data, strengthen retention and manage migration ethically. Yet by January 2026, Nigeria Health Watch found that the policy still lacked clear budget lines and time-bound deliverables. Its verdict was blunt: “A policy without budget lines and clear, time-bound deliverables will stall.”
At regional level, African health ministers meeting at the WHO Regional Committee in Addis Ababa this year adopted the Africa Health Workforce Agenda 2026-2035. It aims to educate, employ and retain at least three million more health workers by 2035, and to cut average health worker unemployment from 27% to 13%.
I welcome both. But targets are a planting calendar, not a harvest. What matters is whether finance ministries create the posts.
In practice, I would ask every ministry three questions:
- Do we know who we trained and where they are? Many countries cannot say how many of their graduates are working, unemployed or abroad. Without a live registry, you cannot plan a single post. That is the kind of practical research and data work that pays for itself.
- Are training places matched to funded posts? Expanding schools without expanding payrolls simply grows the unemployed pool. Plan intakes with the treasury in the room.
- Does training prepare people for the work they will actually do? WHO estimates that health workers in the region correctly diagnose about 62% of cases. Capability, not just headcount, is the goal. As I argued in From training to capability, certificates show that learning happened; practice shows whether it worked.
Reap what we sow
The Bible puts it simply: “whatsoever a man soweth, that shall he also reap” (Galatians 6:7). Africa has sown well. We have built nursing schools and medical colleges and filled them with talented young people.
Now we must do the harder, less glamorous work of bringing in the harvest: posts, pay, supervision and careers worth staying for.
The neighbours are not the problem. The empty basket is.
At Praxis, our education and training and advisory work help institutions plan, train and keep the people they depend on. If you are working on that challenge, let us talk.
Simon Aseno
Simon Aseno is President and CEO of Praxis Global Institute, where he leads work connecting research, technology, education and advisory to strengthen people, systems and institutions.
Facing a similar challenge in your institution?
We work with teams on research, data, digital systems, and learning that hold up in practice.